Sudden electric shocks in my face
They peak in seconds and can come in bursts, often in the cheek, upper lip, teeth or jaw.

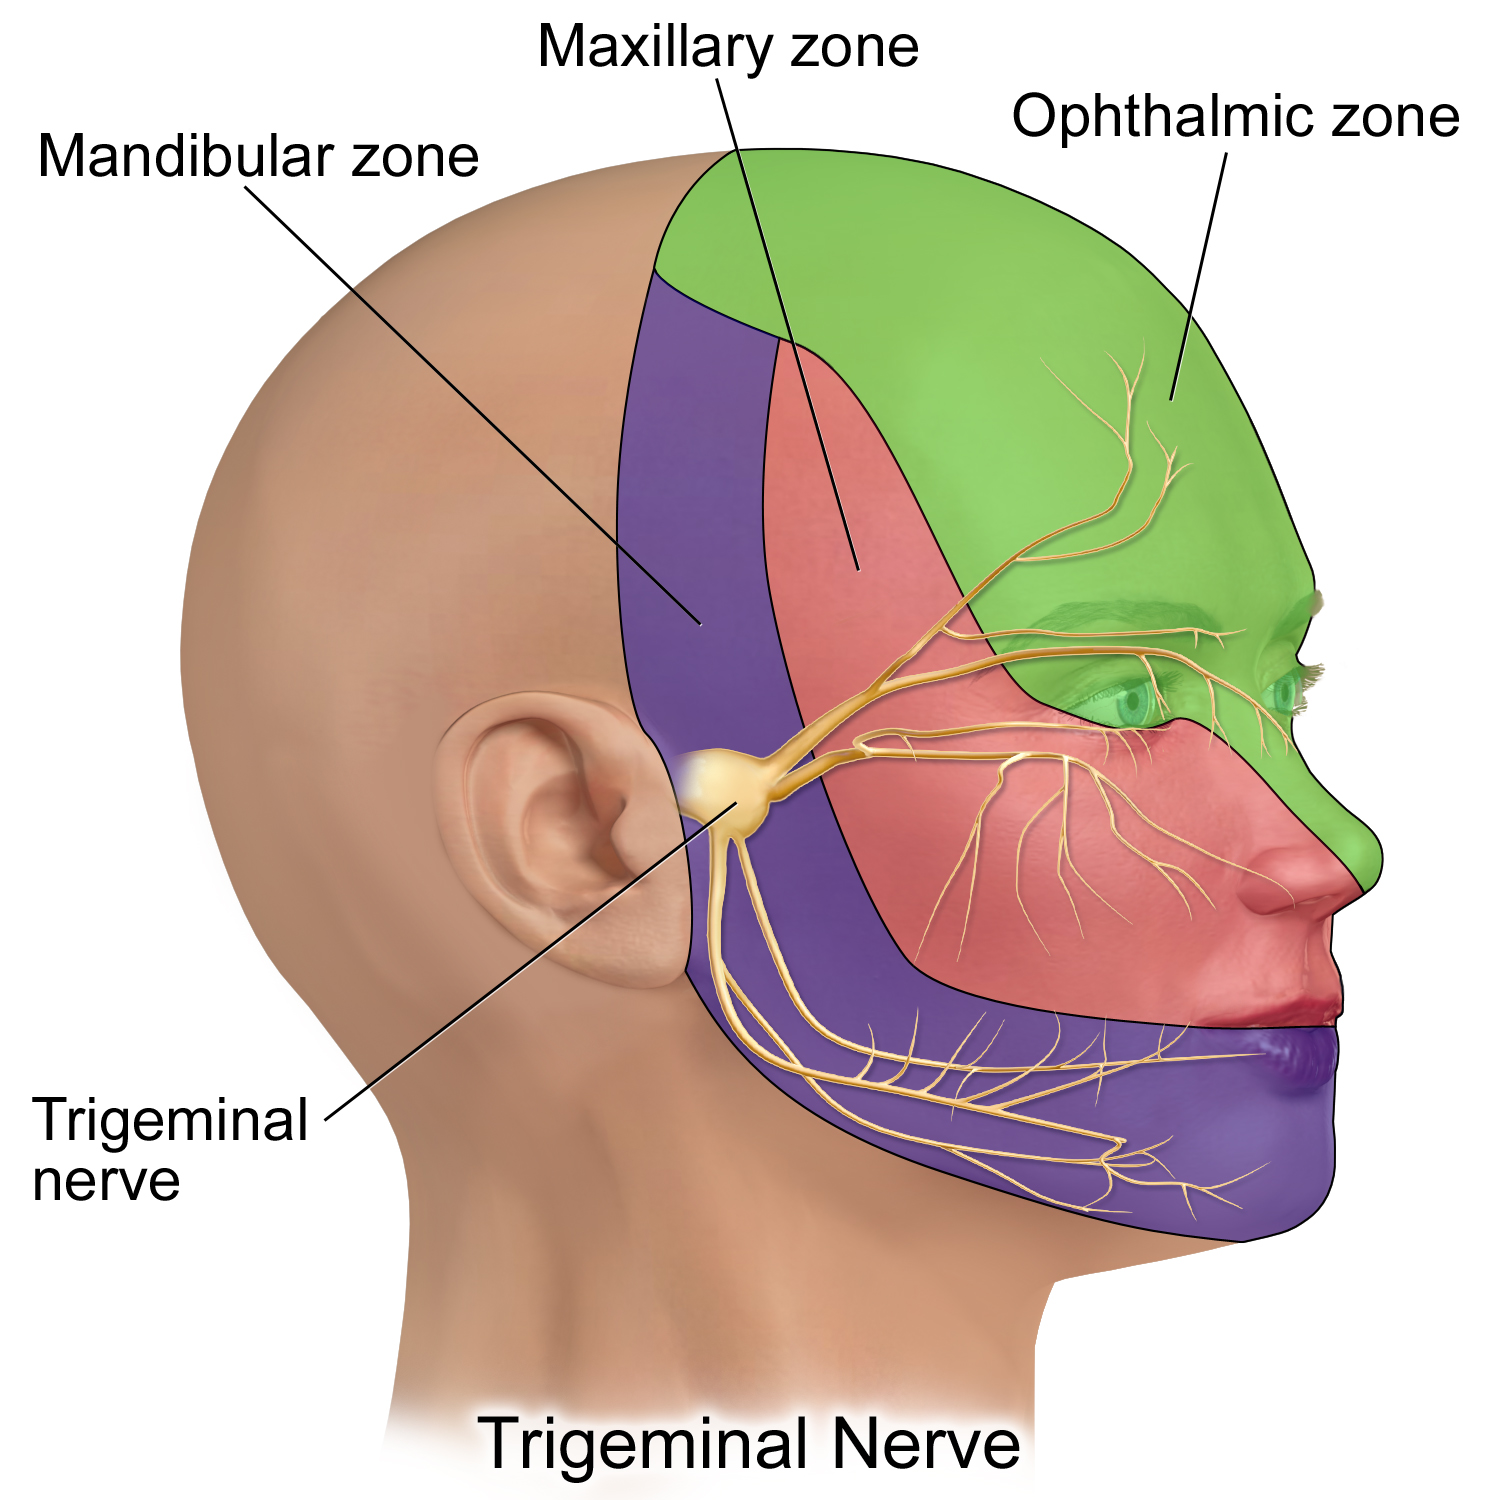
The pain arrives as a stab or an electric shock on one side of the face. It lasts seconds, sometimes in clusters, and usually lands in the cheek, upper lip, teeth or jaw. Chewing, talking, brushing your teeth or cold air can set it off. Between attacks, you may start eating, speaking and washing your face carefully to avoid the next one.
The trigeminal nerve carries feeling from the face in three branches. One serves the forehead and eye, one the cheek and upper teeth, and one the jaw and lower teeth. In trigeminal neuralgia, one or more branches sends pain signals far too easily. Where those signals arrive in the brainstem, the system can also become amplified, so ordinary touch registers as an attack.
I use two tools here. Electroacupuncture is for the nerve, and dry needling, a form of acupuncture, is for jaw and neck muscles that guard. Treatment is gentle and built around your trigger zones, the spots where a light touch sets off pain. I place fine needles near the affected trigeminal branch, away from those spots. A gentle current then aims to change how that branch is signaling. The brainstem’s trigeminal relay extends into the upper neck, so I also work there to help quiet that amplification.
Most people take an anticonvulsant from their neurologist. Some have had an MRI or are weighing a procedure such as microvascular decompression. Medication often reduces attacks, but side effects can limit the dose and breakthrough pain is common. An MRI may show a blood vessel touching the nerve, yet the severity of pain does not always match the scan. These treatments work on the nerve’s chemistry or structure, and electroacupuncture adds a way to work on how it is signaling.
I ask where each attack starts, what sets it off, how often attacks come, and what your neurologist has prescribed. Then the exam:
I work alongside neurologists, neurosurgeons and dentists. If anything during the exam suggests going back to one of them, I’ll let you know and send them my findings.
Depending on how severe the attacks are and how you respond, I plan either two sessions a week across six weeks or three a week across four. A sensitized trigeminal nerve tends to settle better with steady, gentle input than with long gaps. Once the drop in attacks holds, appointments thin out, and I can lighten the pace if your face needs it.
It can’t promise to end the attacks. The aim is to help ease how strong and frequent they are and to make everyday triggers easier to tolerate. It is used alongside medication and neurology care, not instead of them.
I work to avoid that. Needles go away from your trigger zones, the current stays gentle, and the first visits are light. If a spot or setting seems to provoke pain, I change it.
Usually a mix, since the nerve and the brainstem are often both involved. Gentle current beside the irritable branch works on that branch directly. Needles at the top of the neck target the relay that turns the pain up. Tight jaw and neck muscles are eased as well.
Yes. Whether a procedure fits is up to your neurologist and neurosurgeon. I can treat while you weigh that decision and keep them informed of what I see.
Call 911 for facial droop along with weakness in an arm or leg, slurred speech, trouble walking or confusion. These are stroke signs. Get prompt medical care for new numbness in the face, double vision, trouble swallowing, fever, or a sudden change from your usual pain pattern.
Adults with pelvic floor, nerve and orthopedic pain, along with neurological conditions. Most of my patients come to me after other care hasn't fully settled things. If you're looking for general wellness acupuncture, I'm not the right fit.
We review your history and what you've already tried. I assess the muscles and nerves involved, and you're treated the same day.
It depends on the condition. Pelvic and orthopedic plans usually run 4 to 6 weeks. Neurological plans are usually 2 visits a week for 6 weeks or 3 a week for 4. After that, visits space out so the changes hold. These are typical timelines, not promises.
Yes. I work alongside doctors, physical therapists and specialists. If something I find needs a closer look from one of them, I'll tell you.
I'm an out-of-network provider. You pay at the time of your visit, and my office submits the claim so any reimbursement comes to you. Free benefit checks are available before your first visit through the verification form, and HSA and FSA cards work. I don't take Medicare or Medicaid, though some Medicare Advantage plans reimburse out-of-network care. Full insurance details
Yes. I treat adults, teens and children, though I don't specialize in infants or toddlers.
Yes. Book a free discovery call to ask your questions and see whether we're a good fit.
Dry needling is a form of acupuncture. Fine needles go into tight bands of muscle and trigger points to lower muscle tension and change how the area is signaling.
You may feel a brief twitch or a deep ache as the needle reaches tight muscle. It passes quickly, and any soreness afterward usually fades within a day or two.
It's generally safe with a properly trained practitioner. Needles are sterile and single-use, and I check your health history first, including blood thinners. In New York, dry needling can only be performed by licensed acupuncturists, MDs and DOs. Physical therapists and chiropractors aren't permitted to perform it.
Eat something light beforehand and wear loose clothing that lets me reach the area being treated.
Usually not. Ultrasound helps in a few specific cases, but it hasn't been shown to improve results for common trigger points. A careful hands-on exam is what guides the needle. More on ultrasound-guided dry needling
Dry needling aimed at the pelvic floor and the hip and abdominal muscles around it, for pain, tension and urinary symptoms driven by those muscles and their nerves. More on pelvic floor dry needling
Sometimes, depending on the muscles involved, and you'll be draped throughout. Treatment always follows your consent and comfort. I don't do internal exams or internal treatment.
No, though it helps if you've already seen a doctor or pelvic floor physical therapist. Bring any notes or imaging you have.
Completely. I've heard it all, and there's no judgment here, just a straightforward conversation so we can treat what's going on.
Yes, I treat adults of every gender and identity. After gender-affirming surgery involving the pelvis, bring your surgical notes and we'll decide together what fits.
We also offer house calls and after-hours appointments by arrangement.
Private Access & House Calls →Ready when you are.
Limited spots each week — book now to reserve yours.

118 W. 72nd St, Rear Lobby, New York, NY 10023
Evidence-based acupuncture and dry needling on the Upper West Side. From chronic pain and headaches to pelvic floor dysfunction, Dr. Jordan Barber pairs the highest level of training with care that actually listens.

Member Clinic
An independent practice and member of New York Acupuncture Group, sharing clinical space and operations in Manhattan.
This site does not provide medical advice. Always consult a qualified healthcare professional before making changes to your health. Read our full disclaimer.