Pain that changes with stress or position
Often worse after long sitting, commuting or hard training, and briefly better with heat, movement or a change of position.

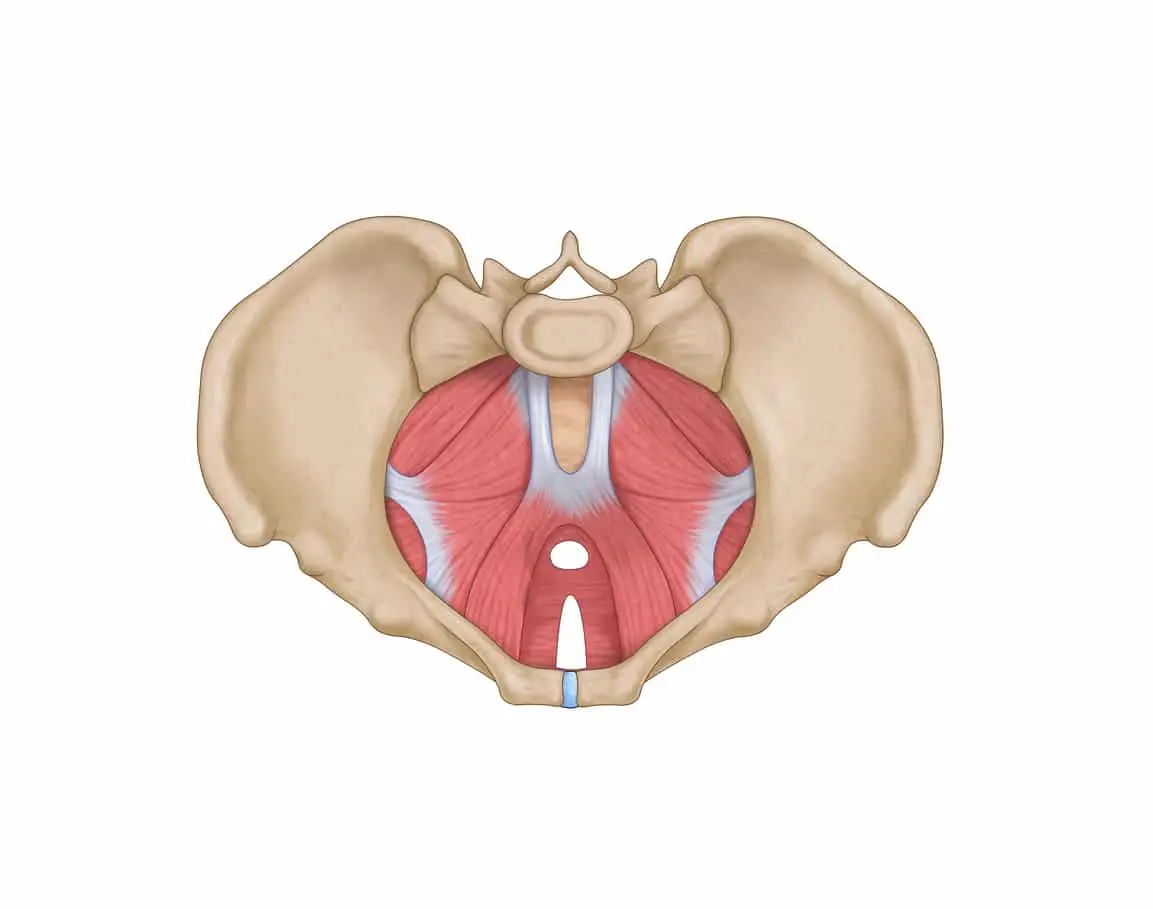
You may notice pelvic pain that rises with stress or sitting. Some people feel urgency soon after urinating, or have trouble starting to urinate or have a bowel movement. Sex or pelvic exams may hurt.
Pelvic floor muscle hypertonia means the pelvic floor holds too much tension at rest, or tightens too early and too hard. Most people aren’t tight all the time. The pelvic floor grips during stress, sitting, lifting, sex, urination or even breathing. Over time that can irritate nearby nerves and create trigger points, which are tight spots that send pain elsewhere.
I treat the muscles involved with dry needling, a form of acupuncture. If the obturator internus or piriformis is squeezing the pudendal or posterior femoral cutaneous nerve, I needle that muscle to give the nerve space. The aim is to help the pelvic floor let go and coordinate again, rather than forcing it with stretching or more strengthening.
Most people have had imaging, medication, and often a strengthening or stretching program. Imaging rarely shows muscle tension, trigger points or nerve irritation. Medication may quiet pain signals without changing the guarding. Strengthening may not help when the muscle can’t relax in the first place. If you’ve worked on relaxation in pelvic floor PT, needling the tight muscle directly is something new. PTs and chiropractors in New York aren’t permitted to dry needle.
I start by asking what sets off your symptoms, how your bladder and bowels behave, and what testing you’ve had. Then the exam:
I coordinate with your doctors and pelvic floor PT. If a finding suggests one of them should recheck something, such as bowel or bladder changes, I’ll tell you and share the details.
Not necessarily. High tone is often a guarding and coordination problem rather than a flexibility problem. Aggressive stretching can irritate sensitive tissue or nerves. A better start is finding which muscles are overworking and why.
Yes. A muscle that holds tension all the time loses range and timing, which can look like weakness. I usually work on relaxation and coordination first. Strength comes after, without bringing the clenching back.
It aims to reduce trigger point activity and lower protective tension. I target the muscles found on exam, including the pelvic floor, inner thigh, deep glutes and hip rotators. As those muscles soften, the pudendal and posterior femoral cutaneous nerves get more room. That makes breathing and movement work easier to build on.
Many people start with 1 to 2 visits a week for a short period, then taper as tension and coordination improve. For high pelvic floor tone, that course usually covers 4 to 6 weeks. I review progress regularly so the plan stays efficient.
No. Tension, trigger points and nerve sensitivity don’t show on standard tests. Stress can increase guarding, but the pattern is still physical and can be treated.
See a doctor promptly for fever, suspected infection, blood in your urine or stool, or unexplained vaginal bleeding. The same goes for new bladder or bowel incontinence, spreading numbness or weakness, severe night pain, or rapidly worsening symptoms. My care works best once these have been ruled out.
Adults with pelvic floor, nerve and orthopedic pain, along with neurological conditions. Most of my patients come to me after other care hasn't fully settled things. If you're looking for general wellness acupuncture, I'm not the right fit.
We review your history and what you've already tried. I assess the muscles and nerves involved, and you're treated the same day.
It depends on the condition. Pelvic and orthopedic plans usually run 4 to 6 weeks. Neurological plans are usually 2 visits a week for 6 weeks or 3 a week for 4. After that, visits space out so the changes hold. These are typical timelines, not promises.
Yes. I work alongside doctors, physical therapists and specialists. If something I find needs a closer look from one of them, I'll tell you.
I'm an out-of-network provider. You pay at the time of your visit, and my office submits the claim so any reimbursement comes to you. Free benefit checks are available before your first visit through the verification form, and HSA and FSA cards work. I don't take Medicare or Medicaid, though some Medicare Advantage plans reimburse out-of-network care. Full insurance details
Yes. I treat adults, teens and children, though I don't specialize in infants or toddlers.
Yes. Book a free discovery call to ask your questions and see whether we're a good fit.
Dry needling is a form of acupuncture. Fine needles go into tight bands of muscle and trigger points to lower muscle tension and change how the area is signaling.
You may feel a brief twitch or a deep ache as the needle reaches tight muscle. It passes quickly, and any soreness afterward usually fades within a day or two.
It's generally safe with a properly trained practitioner. Needles are sterile and single-use, and I check your health history first, including blood thinners. In New York, dry needling can only be performed by licensed acupuncturists, MDs and DOs. Physical therapists and chiropractors aren't permitted to perform it.
Eat something light beforehand and wear loose clothing that lets me reach the area being treated.
Usually not. Ultrasound helps in a few specific cases, but it hasn't been shown to improve results for common trigger points. A careful hands-on exam is what guides the needle. More on ultrasound-guided dry needling
Dry needling aimed at the pelvic floor and the hip and abdominal muscles around it, for pain, tension and urinary symptoms driven by those muscles and their nerves. More on pelvic floor dry needling
Sometimes, depending on the muscles involved, and you'll be draped throughout. Treatment always follows your consent and comfort. I don't do internal exams or internal treatment.
No, though it helps if you've already seen a doctor or pelvic floor physical therapist. Bring any notes or imaging you have.
Completely. I've heard it all, and there's no judgment here, just a straightforward conversation so we can treat what's going on.
Yes, I treat adults of every gender and identity. After gender-affirming surgery involving the pelvis, bring your surgical notes and we'll decide together what fits.
We also offer house calls and after-hours appointments by arrangement.
Private Access & House Calls →Ready when you are.
Limited spots each week — book now to reserve yours.

118 W. 72nd St, Rear Lobby, New York, NY 10023
Evidence-based acupuncture and dry needling on the Upper West Side. From chronic pain and headaches to pelvic floor dysfunction, Dr. Jordan Barber pairs the highest level of training with care that actually listens.

Member Clinic
An independent practice and member of New York Acupuncture Group, sharing clinical space and operations in Manhattan.
This site does not provide medical advice. Always consult a qualified healthcare professional before making changes to your health. Read our full disclaimer.